All content on this site is intended for healthcare professionals only. By acknowledging this message and accessing the information on this website you are confirming that you are a healthcare professional.
The PsOPsA Hub website uses a third-party service provided by Google that dynamically translates web content. Translations are machine generated, so may not be an exact or complete translation, and the PsOPsA Hub cannot guarantee the accuracy of translated content. The PsOPsA Hub and its employees will not be liable for any direct, indirect, or consequential damages (even if foreseeable) resulting from use of the Google Translate feature. For further support with Google Translate, visit Google Translate Help.


The PsOPsA Hub is an independent medical education platform. This activity is supported by an educational grant from Lilly. Funders are allowed no direct influence on our content.
Now you can support HCPs in making informed decisions for their patients
Your contribution helps us continuously deliver expertly curated content to HCPs worldwide. You will also have the opportunity to make a content suggestion for consideration and receive updates on the impact contributions are making to our content.
Find out more
Create an account to access:
Bookmark & personalize site content
Receive alerts for new content in your areas of interest
View psoriasis and psoriatic arthritis content recommended for you
IL-23/IL-17 axis in psoriatic disease: From pathogenesis to personalized treatment
Do you know... Which of these drugs is a dual IL-17A/F inhibitor approved for the treatment of both PsO and PsA?
Introduction
Psoriasis is a chronic, immune-mediated inflammatory disease in which dysregulation of the interleukin (IL)-23/IL-17 axis plays a pivotal role. Genetic and environmental factors trigger keratinocyte stress, initiating an inflammatory cascade that activates plasmacytoid dendritic cells (pDCs) and promotes the release of pro-inflammatory mediators.1,2 This, in turn, leads to activation of myeloid dendritic cells (mDCs) and production of IL-12, IL-23, and tumor necrosis factor (TNF)-α. IL-23 is a key driver of T helper 17 (Th17) responses and induces secretion of IL-17, which stimulates keratinocytes to release antimicrobial peptides, cytokines, and chemokines, thereby driving keratinocyte proliferation and the formation of psoriatic plaques (Figure 1).1,2
Figure 1. The role of the IL-23/IL-17 axis in the pathogenesis of psoriatic disease*
.png)
IL-23/IL-17 axis as a therapeutic target in psoriatic disease
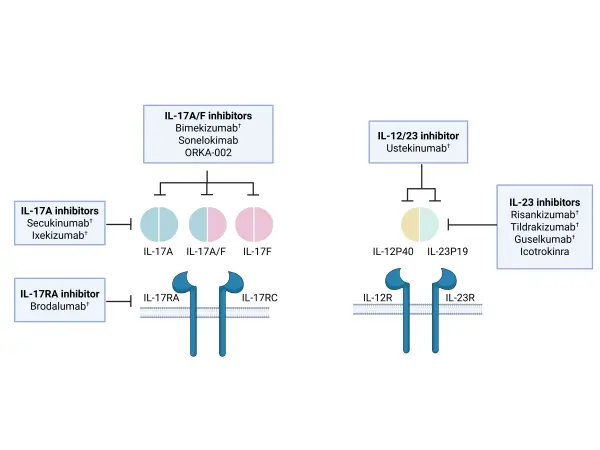
Among the six identified IL-17 isoforms, IL-17A and IL-17F are considered the most pathogenic in psoriasis.4 The interaction between IL-17A/A, IL-17A/F, and IL-17F/F cytokines, and their receptors IL-17RA and IL-17RC, drives the immune response.2 Figure 2 illustrates the therapeutic targets of biologic agents directed against the IL-17/IL-23 pathway. IL-17 pathway inhibition may be achieved through selective inhibition of IL-17A (secukinumab, ixekizumab), blockade of the IL-17RA (brodalumab), or dual inhibition of IL-17A and IL-17F (bimekizumab, sonelokimab, ORKA-002).2,5,6 IL-23 inhibitors act by targeting the shared IL-12/23 p40 subunit (ustekinumab) or the IL-23 p19 subunit (risankizumab, guselkumab, tildrakizumab, icotrokinra).2,7
Figure 2. Therapies targeting the IL-23/IL-17 axis in psoriatic disease*
.png)
Several of these biologic agents are approved by the U.S. Food and Drug Administration (FDA) for the treatment of plaque psoriasis (PsO) and psoriatic arthritis (PsA), reflecting their established efficacy and safety profiles in phase III trials (Table 1).16–38 IL-17A inhibitors such as secukinumab and ixekizumab, as well as the IL-17RA blocker brodalumab, are approved for moderate-to-severe PsO, with secukinumab and ixekizumab also indicated for PsA.8–10 The dual IL-17A/IL-17F inhibitor bimekizumab has been more recently approved for both PsO and PsA,11 while sonelokimab and ORKA-002 remain investigational.5,6 Watch a discussion by the PsOPsA Hub Steering Committee to gain further insights into the clinical implications of IL-17A/F dual inhibitors in the treatment of psoriatic disease.
Among IL-23 inhibitors, ustekinumab was the first to gain FDA approval through its dual targeting of IL‑12/23 p40,12 followed by the selective IL‑23p19 inhibitors guselkumab, risankizumab and tildrakizumab in moderate-to-severe PsO, with ustekinumab, guselkumab, and risankizumab also approved for the treatment of active PsA.13–15 Emerging agents like icotrokinra are undergoing clinical development, underscoring the continued evolution of targeted therapy within the IL-23/IL-17 axis.
Table 1. Efficacy of FDA-approved IL-17, IL-12/23, and IL-23 inhibitors for psoriatic disease*
| Agent | Trial | Population | Primary endpoints |
| IL-17RA inhibitors | |||
| Brodalumab | AMAGINE-1 (NCT01708590)16 | Patients with moderate-to-severe PsO (N = 661) | PASI75 at Week 12: sPGA 0/1 at Week 12: |
| AMAGINE-2 (NCT01708603)17 | Patients with moderate-to-severe PsO (N = 1,831) | PASI75 at Week 12: sPGA 0/1 at Week 12: | |
| AMAGINE-3 (NCT01708629)17 | Patients with moderate-to-severe PsO (N = 1,881) | PASI75 at Week 12: sPGA 0/1 at Week 12: | |
| IL-17A inhibitors | |||
| Secukinumab | ERASURE (NCT01365455)18 | Patients with moderate-to-severe PsO (N = 738) | PASI75 at Week 12: IGA 0/1 at Week 12: |
| FIXTURE (NCT01358578)18 | Patients with moderate-to-severe PsO (N = 1,306) | PASI75 at Week 12: IGA 0/1 at Week 12: | |
| FUTURE 1 (NCT01392326)19 | Patients with PsA (N = 606) | ACR20 at Week 24: Secukinumab 150 mg: 50.0% Secukinumab 75 mg: 50.5% Placebo: 17.3% (p < 0.001) | |
| FUTURE 2 (NCT01752634)20 | Patients with PsA (N = 397) | ACR20 at Week 24: Secukinumab 300 mg: 54.0% Secukinumab 150 mg: 51.0% Placebo: 15.0% (p < 0.0001) | |
| Ixekizumab | UNCOVER-1 (NCT01474512)21 | Patients with moderate-to-severe PsO (N = 1,296) | PASI75 at Week 12: sPGA 0/1 at Week 12: |
| SPIRIT-P1 (NCT01695239)22 | Patients with active PsA naïve to biologic therapy (N = 417) | ACR20 at Week 24: Ixekizumab Q2W: 62.1% Ixekizumab Q4W: 57.9% Placebo: 30.2% (p ≤ 0.001) | |
| SPIRIT-P2 (NCT02349295)23 | Patients with active PsA and TNFi-IR (N = 363) | ACR20 at Week 24: Ixekizumab Q2W: 48.0% Ixekizumab Q4W: 53.0% Placebo: 20.0% (p < 0.0001) | |
| IL-17A/F inhibitors | |||
| Bimekizumab | BE READY (NCT03410992)24 | Patients with moderate-to-severe PsO (N = 435) | PASI90 at Week 16: IGA 0/1 at Week 16: |
| BE VIVID (NCT03370133)25 | Patients with moderate-to-severe PsO (N = 567) | PASI90 at Week 16: Bimekizumab 320 mg Q4W: 85.0% Ustekinumab 45/90 mg Q12W: 50.0% (p < 0.0001) Placebo: 5.0% (p < 0.0001) IGA 0/1 at Week 16: Bimekizumab 320 mg Q4W: 84.0% Ustekinumab 45/90 mg Q12W: 53.0% (p < 0.0001) Placebo: 5.0% (p < 0.0001) | |
| BE SURE (NCT03412747)26 | Patients with moderate-to-severe PsO (N = 478) | PASI90 at Week 16: IGA 0/1 at Week 16: | |
| BE OPTIMAL (NCT03895203)27 | Patients with PsA naïve to biologics (N = 852) | ACR50 at Week 16: Bimekizumab 160 mg SC Q4W: 44.0% Placebo: 10.0% (p < 0.0001) | |
| BE COMPLETE (NCT03896581)28 | Patients with PsA and TNFi-IR (N = 400) | ACR50 at Week 16: Bimekizumab 160 mg SC Q4W: 43% Placebo: 7.0% (p < 0.0001) | |
| IL-12/23 inhibitors | |||
| Ustekinumab | PHOENIX 2 (NCT00307437)29 | Patients with moderate-to-severe PsO (N = 1,230) | PASI75 at Week 12: Ustekinumab 45 mg: 66.7% Ustekinumab 90 mg: 75.7% Placebo: 3.7% (p < 0.0001) |
| PSUMMIT 1 (NCT01009086)30 | Patients with PsA (N = 615) | ACR20 at Week 24: Ustekinumab 45 mg: 42.4% Ustekinumab 90 mg: 49.5% Placebo: 22.8% (p < 0.0001) | |
| PSUMMIT 2 (NCT01077362)31 | Patients with PsA with and without prior exposure to anti-TNF (N = 312) | ACR20 at Week 24: Ustekinumab: 43.8% Placebo: 20.2% (p < 0.001) | |
| IL-23 inhibitors | |||
| Risankizumab | ultIMMa-1 (NCT02684370)32 | Patients with moderate-to-severe plaque psoriasis (N = 506) | PASI90 at Week 16: sPGA 0/1 at Week 16: |
| ultIMMa-2 (NCT02684357)32 | Patients with moderate-to-severe plaque psoriasis (N = 491) | PASI90 at Week 16: sPGA 0/1 at Week 16: | |
| KEEPsAKE-1 (NCT03675308)33 | Patients with PsA and csDMARD-IR (N = 964) | ACR20 at Week 24: Risankizumab: 57.3% Placebo: 33.5% (p < 0.001) | |
| KEEPsAKE-2 (NCT03671148)34 | Patients PsA and Bio-IR and/or csDMARD-IR (N = 444) | ACR20 at Week 24: Risankizumab: 51.3% Placebo: 26.5% (p < 0.001) | |
| Tildrakizumab | reSURFACE 1 (NCT01722331)35 | Patients with chronic PsO (N = 772) | PASI75 at Week 12: Tildrakizumab 200 mg: 62.0% Tildrakizumab 100 mg: 64.0% Placebo: 6.0% (p < 0.0001) PGA 0/1 at Week 12: Tildrakizumab 200 mg: 59.0% Tildrakizumab 100 mg: 58.0% Placebo: 7.0% (p < 0.0001) |
| reSURFACE 2 (NCT01729754)35 | Patients with chronic PsO (N = 1,090) | PASI75 at Week 12: Tildrakizumab 200 mg: 66.0% Tildrakizumab 100 mg: 61.0% Placebo: 6.0% (p < 0.0001) Etanercept: 48.0% (p < 0.0001 for 200 mg vs etanercept and p = 0.0010 for 100 mg vs etanercept) PGA 0/1 at Week 12: Tildrakizumab 200 mg: 59.0% Tildrakizumab 100 mg: 55.0% Placebo: 7.0% (p < 0.0001) Etanercept: 48.0% (p = 0.0031 for 200 mg vs etanercept and p = 0.0663 for 100 mg vs etanercept) | |
| Guselkumab | VOYAGE 1 (NCT02207231)36 | Patients with moderate-to-severe PsO (N = 837) | IGA 0/1 at Week 16: PASI90 at Week 16: |
| VOYAGE 2 (NCT02207244)37 | Patients with moderate-to-severe PsO (N = 992) | IGA 0/1 at Week 16: PASI90 at Week 16: | |
| NAVIGATE (NCT02203032)38 | Patients with moderate-to-severe PsO and IR to ustekinumab (N = 871) | Number of visits at which patients achieved IGA 0/1 and ≥2 grade improvement (Week 28–40): Guselkumab: 1.5 Ustekinumab: 0.7 (p < 0.001) | |
| ACR20/50, ≥20%/≥50% improvement from baseline in American College of Rheumatology response criteria; csDMARD, conventional synthetic disease-modifying anti-rheumatic drug; IGA 0/1, Investigator’s Global Assessment score of 0 (clear) or 1 (almost clear); IR, inadequate response; PASI75/90/100, ≥75%/≥90%/100% improvement from baseline in Psoriasis Area and Severity Index; PsA, psoriatic arthritis; PsO, plaque psoriasis; Q4W, every 4 weeks; Q12W, every 12 weeks; SC, subcutaneous; sPGA 0/1, static Physician’s Global Assessment 0 or 1; TNF, tumor necrosis factor α; TNFi, TNF inhibitor. *Data from Papp et al.,16 Lebwohl et al.,17 Langley et al.,18 Mease et al.,19 McInnes et al.,20 Gordon et al.,21 Mease et al.,22 Nash et al.,23 Gordon et al.,24 Reich et al.,25 Warren et al.,26 McInnes et al.,27 Merola et al.,28 Papp et al.,29 McInnes et al.,30 Ritchlin et al.,31 Gordon et al.,32 Kristensen et al.,33 Östör et al.,34 Reich et al.,35 Blauvelt et al.,36 Reich et al.,37 and Langley et al.38 | |||
Comparative efficacy of IL-23/IL-17 inhibitors
Given the growing number of biologic treatment options for psoriasis, selecting the most appropriate therapy remains a key clinical challenge. Several comparative trials between these agents, as summarized in Table 2, provide valuable insights to guide clinicians in tailoring therapy to individual patient needs. Clinical evidence indicates that IL-17 inhibitors are associated with a more rapid onset of response compared with IL-23 inhibitors, whereas IL-23 blockade demonstrates durable responses.3 In addition, dual inhibition of IL-17A/F appears to offer superior efficacy than with IL-17A inhibition alone.3 In the BE RADIANT trial, bimekizumab administered over 16 weeks achieved greater skin clearance than secukinumab in patients with moderate-to-severe psoriasis (Table 2).39 Although no direct head-to-head trial has evaluated bimekizumab vs secukinumab in PsA, a matching-adjusted indirect comparison suggested a higher likelihood of achieving ACR70 responses with bimekizumab in patients who were biologic-naïve (odds ratio [OR], 2.39; p = 0.008) or those with prior inadequate response to TNF inhibitors (OR, 2.95; p = 0.035).40 However, as IL-17F also plays a role in mucosal immunity, dual IL-17A/F blockade carries an elevated risk of Candida infections than with IL-17A inhibition alone. Accordingly, selection of an appropriate agent should consider individual patient factors, including comorbidities, prior treatment history, and safety profiles.
Table 2. Key head-to-head trials between IL-17/23 inhibitors*
| Comparators | Trial | Patient population | Key findings |
| Brodalumab vs ustekinumab | AMAGINE-2 (NCT01708603)17 | Patients with moderate-to-severe PsO (N = 1,831) | PASI100 at Week 12: Brodalumab 210 mg: 44.0% Ustekinumab: 22.0% (p < 0.001) |
| AMAGINE-3 (NCT01708629)17 | Patients with moderate-to-severe PsO (N = 1,881) | PASI100 at Week 12: Brodalumab 210 mg: 37.0% Ustekinumab: 19.0% (p < 0.001) | |
| Guselkumab vs secukinumab | ECLIPSE (NCT03090100)41 | Patients with moderate-to-severe PsO (N = 1,048) | PASI90 at Week 48: Guselkumab: 84.0% Secukinumab: 70.0% (p < 0.0001) |
| Ixekizumab vs guselkumab | IXORA-R (NCT03573323)42 | Patients with moderate-to-severe PsO (N = 1,027) | PASI100 at Week 12: Ixekizumab: 41.0% Guselkumab: 25.0% (p < 0.001) |
| Risankizumab vs secukinumab | IMMerge (NCT03478787)43 | Patients with moderate-to-severe PsO (N = 327) | PASI90 at Week 52: Risankizumab: 86.6% Secukinumab: 57.1% (p < 0.001) |
| Bimekizumab vs secukinumab | BE RADIANT (NCT03536884)39 | Patients with moderate-to-severe PsO (N = 743) | PASI100 at Week 16: Bimekizumab: 61.7% Secukinumab: 48.9% (p < 0.001) |
| IL, interleukin; PASI90/100, 90%/100% improvement from baseline in Psoriasis Area and Severity Index; PsA, psoriatic arthritis; PsO, plaque psoriasis. *Data from Lebwohl et al.,17 Reich et al.,39 Reich et al.,41 Blauvelt et al.,42 and Warren et al.43 | |||
Future directions
Future research on IL-23/IL-17 inhibitors is focused on leveraging a multi-omics approach to investigate the pathway’s nuanced effects across different cell types and tissues. In addition, there is a need to identify optimal timing for therapy initiation, uncover biomarkers predictive of treatment response, and characterize epigenetic and post-translational modifications influencing disease progression and therapeutic outcomes. These insights may inform personalized treatment strategies, improve prediction of clinical outcomes, and optimize the long-term efficacy and safety of IL-17/IL-23-targeted therapies in psoriatic disease.44
Conclusions
The IL-23/IL-17 axis is central to the pathogenesis of psoriatic disease, and targeting this pathway with biologics has transformed treatment for both PsO and PsA. IL-17 inhibitors offer rapid clinical responses, while IL-23 blockade provides durable outcomes, and dual IL-17A/F inhibition may further enhance efficacy over IL-17 inhibition alone. Future research leveraging multi-omics approaches and biomarker-driven strategies is needed to optimize therapy timing, personalize treatment, and improve long-term efficacy and safety, guiding more precise management of psoriatic disease.
This educational resource is independently supported by UCB. All content was developed by SES in collaboration with an expert steering committee. Funders were allowed no influence on the content of this resource.
References
Zhou X, Chen Y, Cui L, et al. Advances in the pathogenesis of psoriasis: From keratinocyte perspective. Cell Death Dis. 2022;13(1):81. DOI: 10.1038/s41419-022-04523-3
Liu T, Li S, Ying S, et al. The IL-23/IL-17 pathway in inflammatory skin diseases: From bench to bedside. Front Immunol. 2020;11:594735. DOI: 10.3389/fimmu.2020.594735
Brembilla NC, Boehncke WH. Revisiting the interleukin 17 family of cytokines in psoriasis: pathogenesis and potential targets for innovative therapies. Front Immunol. 2023;14:1186455. DOI: 10.3389/fimmu.2023.1186455
Bugaut H, Aractingi S. Major role of the IL17/23 axis in psoriasis supports the development of new targeted therapies. Front Immunol. 2021;12:621956. DOI: 10.3389/fimmu.2021.621956
McInnes IB. Impact of sonelokimab, a novel IL-17A- and IL-17F-inhibiting nanobody, on multidomain clinical outcomes in active psoriatic arthritis: results from the randomized, double-blind, placebo-controlled Phase 2 ARGO trial. Oral Abstract #OP0096. Presented at: European Alliance of Associations for Rheumatology 2025 Congress; Jun 11–14, 2025; Barcelona, ES.
Merola J. Characterization of ORKA-002, a novel extended half-life monoclonal antibody targeting IL-17A/F for the treatment of psoriasis and other indications. Poster #POS0016. EULAR 2025; Jun 11–14, 2025; Barcelona, ES.
Merola JF. Icotrokinra, a targeted oral peptide that selectively blocks the interleukin-23-receptor, for the treatment of moderate-to-severe plaque psoriasis: Results through Week 24 of the phase 3, randomized, double-blind, placebo-controlled ICONIC-LEAD trial. Abstract #POS1072. Presented at: European Alliance of Associations for Rheumatology 2025 Congress; Jun 11–14, 2025; Barcelona, ES.
Brodalumab. Prescribing Information (FDA). 2017. Revised Aug 2024.
Secukinumab. Prescribing Information (FDA). 2015. Updated Aug 2025.
Ixekizumab. Prescribing Information (FDA). 2016. Revised Aug 2024.
Bimekizumab. Prescribing Information (FDA). 2023. Revised Nov 2024.
Ustekinumab. Prescribing Information (FDA). 2009. Revised Jun 2025.
Guselkumab. Prescribing Information (FDA). 2017. Revised Sep 2025.
Risankizumab. Prescribing Information (FDA). 2019. Revised Sep 2025.
Tildrakizumab. Prescribing Information (FDA). 2018. Revised Apr 2024.
Papp KA, Reich K, Paul C, et al. A prospective phase III, randomized, double‐blind, placebo‐controlled study of brodalumab in patients with moderate‐to‐severe plaque psoriasis. Br J Dermatol. 2016;175(2):273-286. DOI: 10.1111/bjd.14493
Lebwohl M, Strober B, Menter A, et al. Phase 3 studies comparing brodalumab with ustekinumab in psoriasis. N Engl J Med. 2015;373(14):1318-1328. DOI: 10.1056/NEJMoa1503824
Langley RG, Elewski BE, Lebwohl M, et al. Secukinumab in plaque psoriasis — results of two phase 3 trials. N Engl J Med. 2014;371(4):326-338. DOI: 10.1056/NEJMoa1314258
Mease PJ, McInnes IB, Kirkham B, et al. Secukinumab inhibition of interleukin-17A in patients with psoriatic arthritis. N Engl J Med. 2015;373(14):1329-1339. DOI: 10.1056/NEJMoa1412679
McInnes IB, Mease PJ, Kirkham B, et al. Secukinumab, a human anti-interleukin-17A monoclonal antibody, in patients with psoriatic arthritis (FUTURE 2): A randomised, double-blind, placebo-controlled, phase 3 trial. Lancet. 2015;386(9999):1137-1146. DOI: 10.1016/S0140-6736(15)61134-5
Gordon KB, Blauvelt A, Papp KA, et al. Phase 3 trials of ixekizumab in moderate-to-severe plaque psoriasis. N Engl J Med. 2016;375(4):345-356. DOI: 10.1056/NEJMoa1512711
Mease PJ, Van Der Heijde D, Ritchlin CT, et al. Ixekizumab, an interleukin-17A specific monoclonal antibody, for the treatment of biologic-naive patients with active psoriatic arthritis: results from the 24-week randomised, double-blind, placebo-controlled and active (adalimumab)-controlled period of the phase III trial SPIRIT-P1. Ann Rheum Dis. 2017;76(1):79-87. DOI: 10.1136/annrheumdis-2016-209709
Nash P, Kirkham B, Okada M, et al. Ixekizumab for the treatment of patients with active psoriatic arthritis and an inadequate response to tumour necrosis factor inhibitors: Results from the 24-week randomised, double-blind, placebo-controlled period of the SPIRIT-P2 phase 3 trial. Lancet. 2017;389(10086):2317-2327. DOI: 10.1016/S0140-6736(17)31429-0
Gordon KB, Foley P, Krueger JG, et al. Bimekizumab efficacy and safety in moderate to severe plaque psoriasis (BE READY): A multicentre, double-blind, placebo-controlled, randomised withdrawal phase 3 trial. Lancet. 2021;397(10273):475-486. DOI: 10.1016/S0140-6736(21)00126-4
Reich K, Papp KA, Blauvelt A, et al. Bimekizumab versus ustekinumab for the treatment of moderate to severe plaque psoriasis (BE VIVID): Efficacy and safety from a 52-week, multicentre, double-blind, active comparator and placebo controlled phase 3 trial. Lancet. 2021;397(10273):487-498. DOI: 10.1016/S0140-6736(21)00125-2
Warren RB, Blauvelt A, Bagel J, et al. Bimekizumab versus adalimumab in plaque psoriasis. N Engl J Med. 2021;385(2):130-141. DOI: 10.1056/NEJMoa2102388
McInnes IB, Asahina A, Coates LC, et al. Bimekizumab in patients with psoriatic arthritis, naive to biologic treatment: A randomised, double-blind, placebo-controlled, phase 3 trial (BE OPTIMAL). Lancet. 2023;401(10370):25-37. DOI: 10.1016/S0140-6736(22)02302-9
Merola JF, Landewé R, McInnes IB, et al. Bimekizumab in patients with active psoriatic arthritis and previous inadequate response or intolerance to tumour necrosis factor-α inhibitors: A randomised, double-blind, placebo-controlled, phase 3 trial (BE COMPLETE). Lancet. 2023;401(10370):38-48. DOI: 10.1016/S0140-6736(22)02303-0
Papp KA, Langley RG, Lebwohl M, et al. Efficacy and safety of ustekinumab, a human interleukin-12/23 monoclonal antibody, in patients with psoriasis: 52-week results from a randomised, double-blind, placebo-controlled trial (PHOENIX 2). Lancet. 2008;371(9625):1675-1684. DOI: 10.1016/S0140-6736(08)60726-6
McInnes IB, Kavanaugh A, Gottlieb AB, et al. Efficacy and safety of ustekinumab in patients with active psoriatic arthritis: 1 year results of the phase 3, multicentre, double-blind, placebo-controlled PSUMMIT 1 trial. Lancet. 2013;382(9894):780-789. DOI: 10.1016/S0140-6736(13)60594-2
Ritchlin C, Rahman P, Kavanaugh A, et al. Efficacy and safety of the anti-IL-12/23 p40 monoclonal antibody, ustekinumab, in patients with active psoriatic arthritis despite conventional non-biological and biological anti-tumour necrosis factor therapy: 6-month and 1-year results of the phase 3, multicentre, double-blind, placebo-controlled, randomised PSUMMIT 2 trial. Ann Rheum Dis. 2014;73(6):990-999. DOI: 10.1136/annrheumdis-2013-204655
Gordon KB, Strober B, Lebwohl M, et al. Efficacy and safety of risankizumab in moderate-to-severe plaque psoriasis (UltIMMa-1 and UltIMMa-2): Results from two double-blind, randomised, placebo-controlled and ustekinumab-controlled phase 3 trials. Lancet. 2018;392(10148):650-661. DOI: 10.1016/S0140-6736(18)31713-6
Kristensen LE, Keiserman M, Papp K, et al. Efficacy and safety of risankizumab for active psoriatic arthritis: 24-week results from the randomised, double-blind, phase 3 KEEPsAKE 1 trial. Ann Rheum Dis. 2022;81(2):225-231. DOI: 10.1136/annrheumdis-2021-221019
Östör A, Van Den Bosch F, Papp K, et al. Efficacy and safety of risankizumab for active psoriatic arthritis: 24-week results from the randomised, double-blind, phase 3 KEEPsAKE 2 trial. Ann Rheum Dis. 2022;81(3):351-358. DOI: 10.1136/annrheumdis-2021-221048
Reich K, Papp KA, Blauvelt A, et al. Tildrakizumab versus placebo or etanercept for chronic plaque psoriasis (reSURFACE 1 and reSURFACE 2): Results from two randomised controlled, phase 3 trials. Lancet. 2017;390(10091):276-288. DOI: 10.1016/S0140-6736(17)31279-5
Blauvelt A, Papp KA, Griffiths CEM, et al. Efficacy and safety of guselkumab, an anti-interleukin-23 monoclonal antibody, compared with adalimumab for the continuous treatment of patients with moderate to severe psoriasis: Results from the phase III, double-blinded, placebo- and active comparator–controlled VOYAGE 1 trial. J Am Acad Dermatol. 2017;76(3):405-417. DOI: 10.1016/j.jaad.2016.11.041
Reich K, Armstrong AW, Foley P, et al. Efficacy and safety of guselkumab, an anti-interleukin-23 monoclonal antibody, compared with adalimumab for the treatment of patients with moderate to severe psoriasis with randomized withdrawal and retreatment: Results from the phase III, double-blind, placebo- and active comparator–controlled VOYAGE 2 trial. J Am Acad Dermatol. 2017;76(3):418-431. DOI: 10.1016/j.jaad.2016.11.042
Langley RG, Tsai T ‐F, Flavin S, et al. Efficacy and safety of guselkumab in patients with psoriasis who have an inadequate response to ustekinumab: Results of the randomized, double‐blind, phase III NAVIGATE trial. Br J Dermatol. 2018;178(1):114-123. DOI: 10.1111/bjd.15750
Reich K, Warren RB, Lebwohl M, et al. Bimekizumab versus secukinumab in plaque psoriasis. N Engl J Med. 2021;385(2):142-152. DOI: 10.1056/NEJMoa2102383
Mease PJ, Warren RB, Nash P, et al. Comparative effectiveness of bimekizumab and secukinumab in patients with psoriatic arthritis at 52 Weeks using a matching-adjusted indirect comparison. Rheumatol Ther. 2024;11(3):817-828. DOI: 10.1007/s40744-024-00652-7
Reich K, Armstrong AW, Langley RG, et al. Guselkumab versus secukinumab for the treatment of moderate-to-severe psoriasis (ECLIPSE): Results from a phase 3, randomised controlled trial. Lancet. 2019;394(10201):831-839. DOI: 10.1016/S0140-6736(19)31773-8
Blauvelt A, Papp K, Gottlieb A, et al. A head‐to‐head comparison of ixekizumab vs. guselkumab in patients with moderate‐to‐severe plaque psoriasis: 12‐week efficacy, safety and speed of response from a randomized, double‐blinded trial. Br J Dermatol. 2020;182(6):1348-1358. DOI: 10.1111/bjd.18851
Warren RB, Blauvelt A, Poulin Y, et al. Efficacy and safety of risankizumab vs. secukinumab in patients with moderate‐to‐severe plaque psoriasis (IMMerge): Results from a phase III, randomized, open‐label, efficacy–assessor‐blinded clinical trial. Br J Dermatol. 2021;184(1):50-59. DOI: 10.1111/bjd.19341
Krueger JG, Eyerich K, Kuchroo VK, et al. IL-23 past, present, and future: A roadmap to advancing IL-23 science and therapy. Front Immunol. 2024;15:1331217. DOI: 10.3389/fimmu.2024.1331217
Please indicate your level of agreement with the following statements:
The content was clear and easy to understand
The content addressed the learning objectives
The content was relevant to my practice
I will change my clinical practice as a result of this content
This content is accurate as of the date of publication and is not updated retrospectively. Please refer to the latest available evidence, guidelines, and relevant regulatory information when making clinical decisions.
More from this series:
.webp)