All content on this site is intended for healthcare professionals only. By acknowledging this message and accessing the information on this website you are confirming that you are a healthcare professional.
The PsOPsA Hub website uses a third-party service provided by Google that dynamically translates web content. Translations are machine generated, so may not be an exact or complete translation, and the PsOPsA Hub cannot guarantee the accuracy of translated content. The PsOPsA Hub and its employees will not be liable for any direct, indirect, or consequential damages (even if foreseeable) resulting from use of the Google Translate feature. For further support with Google Translate, visit Google Translate Help.


The PsOPsA Hub is an independent medical education platform. This activity is supported by an educational grant from Lilly. Funders are allowed no direct influence on our content.
Now you can support HCPs in making informed decisions for their patients
Your contribution helps us continuously deliver expertly curated content to HCPs worldwide. You will also have the opportunity to make a content suggestion for consideration and receive updates on the impact contributions are making to our content.
Find out more
Create an account to access:
Bookmark & personalize site content
Receive alerts for new content in your areas of interest
View psoriasis and psoriatic arthritis content recommended for you
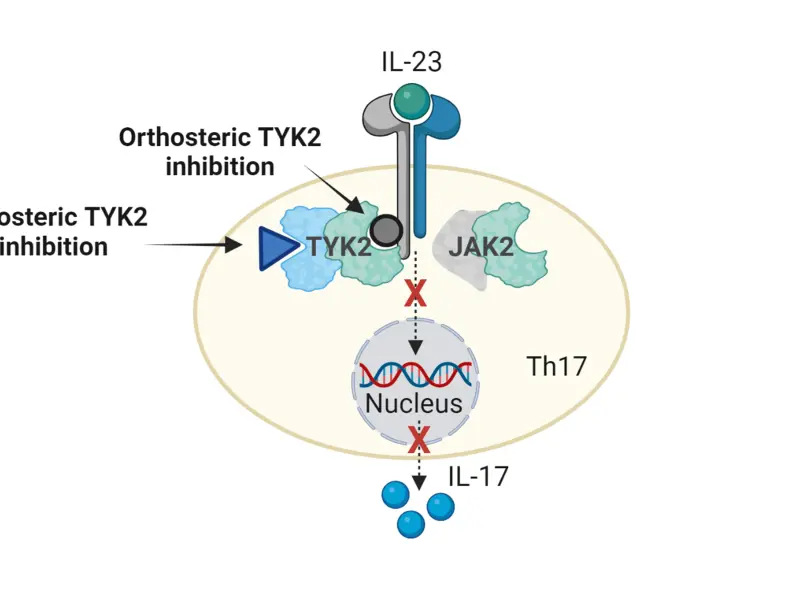
Phase III LATITUDE-PsO-3001 and -3002 trials: Zasocitinib in moderate-to-severe plaque PsO
Results from the randomized, multicenter, phase III LATITUDE-PsO-3001 (NCT06088043) and LATITUDE-PsO-3002 (NCT06108544) trials, evaluating zasocitinib in patients with moderate-to-severe plaque psoriasis (PsO), were presented by Melinda Gooderham at the European Academy of Dermatology and Venereology (EADV) 2026 Congress, September 30 – October 3, 2026, Vienna, AT. In LATITUDE-PsO-3001, patients (N = 693) were randomized 3:1:1 to receive zasocitinib, apremilast, or placebo. In LATITUDE-PsO-3002, patients (N = 1,108) were randomized 2:1:1 to receive zasocitinib, apremilast, or placebo. In both studies, patients receiving placebo were reassigned to receive zasocitinib if they were achieving below ≥75% reduction in Psoriasis Area and Severity Index (PASI75) from Week 16 onward. The co-primary endpoints were the proportion of patients attaining a static Physician’s Global Assessment (sPGA) score of 0/1 and PASI75 at Week 16.
Key data: Zasocitinib improved efficacy outcomes vs apremilast and placebo at all timepoints assessed in both LATITUDE-PsO-3001 (zasocitinib, n = 416; apremilast, n = 137; placebo, n = 140) and LATITUDE-PsO-3002 (zasocitinib, n = 555; apremilast, n = 276; placebo, n = 277). At Week 16, a greater proportion of patients receiving zasocitinib vs apremilast achieved a PASI75 response in LATITUDE-PsO-3001 (75.7% vs 37.2%; p < 0.001) and LATITUDE-PsO-3002 (71.4% vs 33.0%; p < 0.001); significant improvements in response were observed from Week 4 in LATITUDE-PsO-3002 (p < 0.001). At Week 16, 71.4% vs 32.1% of patients receiving zasocitinib vs apremilast attained sPGA 0/1 in LATITUDE-PsO-3001 (p < 0.001) and 69.2% vs 29.7% of patients did so in LATITUDE-PsO-3002 (p < 0.001); significant improvements in response were observed from Week 4 in both LATITUDE-PsO-3001 (p < 0.01) and -3002 (p < 0.001). Improvements with zasocitinib vs apremilast were maintained through Week 24 in both trials (both p < 0.001). In a pooled safety analysis, 69.3% of patients receiving zasocitinib experienced any treatment-emergent adverse event (TEAE), including serious adverse events (SAEs) in 3.6% of patients through Week 24.
Key learning: In the LATITUDE-PsO-3001 and -3002 trials, zasocitinib demonstrated significant improvements in disease activity at Week 24 vs apremilast in patients with moderate-to-severe plaque PsO, with no new safety signals identified. Zasocitinib will be assessed further in additional phase III studies (NCT06550076 and NCT06973291).
References
- Gooderham M. Once-daily oral zasocitinib, a highly selective TYK2 inhibitor, demonstrates rapid improvements in skin clearance, quality of life and psoriasis symptoms in adults with moderate-to-severe plaque psoriasis: results from two randomized phase 3 trials (LATITUDE-PsO-3001 and 3002). Oral Abstract #FC05.1F. Presented at: European Academy of Dermatology and Venereology Congress 2026, September 30 – October 3, 2026, Vienna, AT.
Please indicate your level of agreement with the following statements:
The content was clear and easy to understand
The content addressed the learning objectives
The content was relevant to my practice
I will change my clinical practice as a result of this content
This content is accurate as of the date of publication and is not updated retrospectively. Please refer to the latest available evidence, guidelines, and relevant regulatory information when making clinical decisions.

.webp)